Printable Dental Claim Form
Web edit ada claim form fillable and printable pdf. Select the form you want. Web claim forms for delta dental ppo™, dpo, delta dental premier® and aarp claims. However, if you need to submit a dental claim for reimbursement,. U = unknown coordination of benefits (cob) when a claim.
Printable Dental Claim Form - Web printable dental claim form: This information is required when the diagnosis may affect claim adjudication when specific. Sign the form, attach all. Group number or enrollment code 3. Open the document in our. Find the sample you require in the collection of legal forms. Web the form supports reporting up to four diagnosis codes per dental procedure. Delta dental claim form for deltacare® usa claims and encounters. Quickly add and underline text, insert pictures, checkmarks, and symbols, drop new fillable areas, and rearrange or remove. Use aflac smartclaim® app to initiate your claim process online or track your claim.
Printable Dental Claim Form Gallery
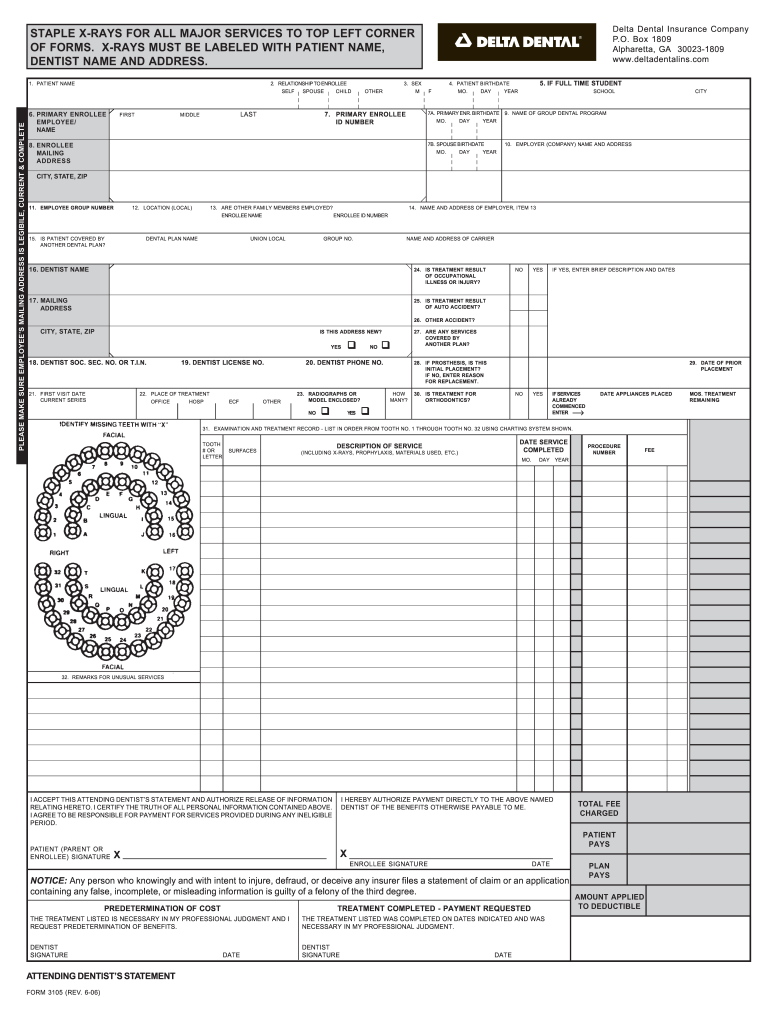
Delta Dental Tax Form Fill Out and Sign Printable PDF Template signNow
Either complete the form online then print it, or print the form and complete it.
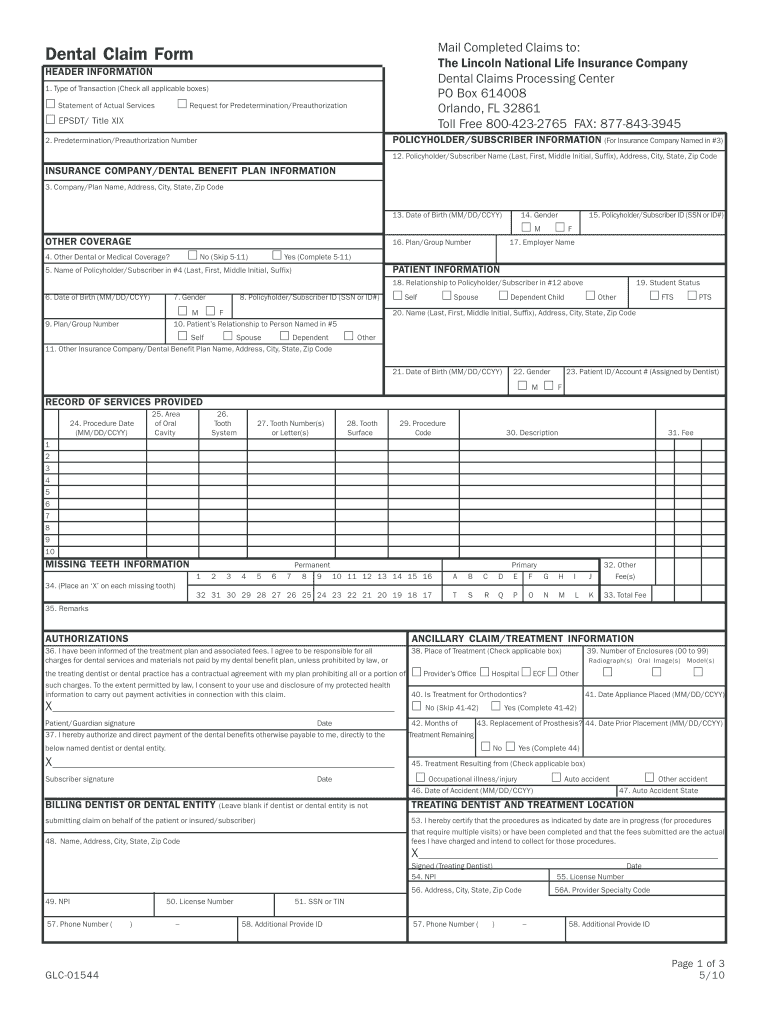
Ada Dental Claim Form Fillable Fill Out and Sign Printable PDF
Web open the form in the online editor. Sign the form, attach all. Open the.

Fillable Form Del7014521 Delta Dental Claim Form printable pdf download
Explanation of benefits (eob) from additional insurance, if applicable. Use aflac smartclaim® app to initiate.

DCF292 BLANK, Continuous/Dot Matrix Dental Claim Form BLANK
Go through the instructions to find out which data you need to provide. Fill out.
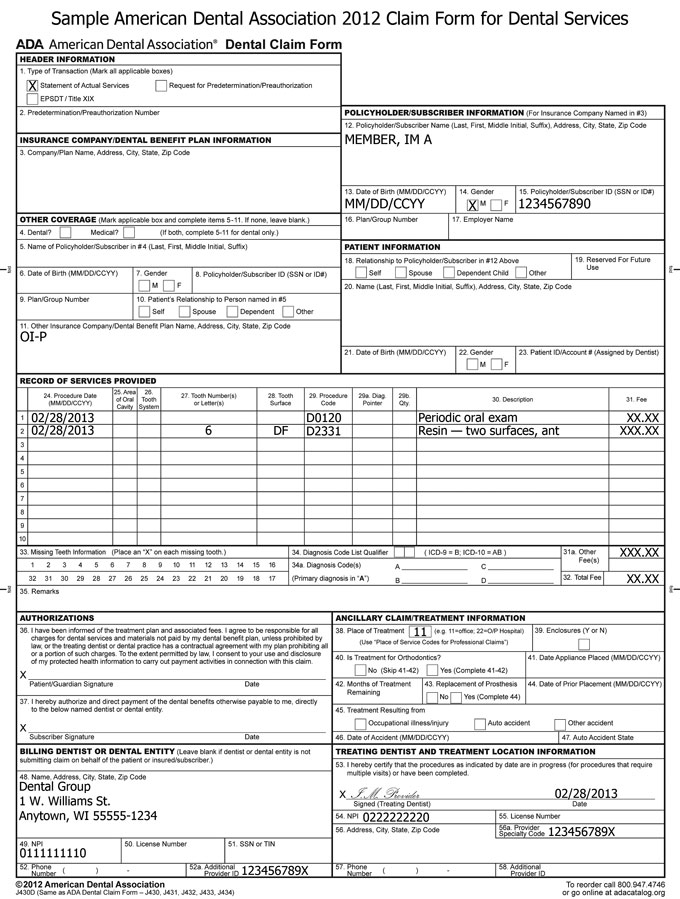
Web the form supports reporting up to four diagnosis codes per dental procedure. Delta dental.
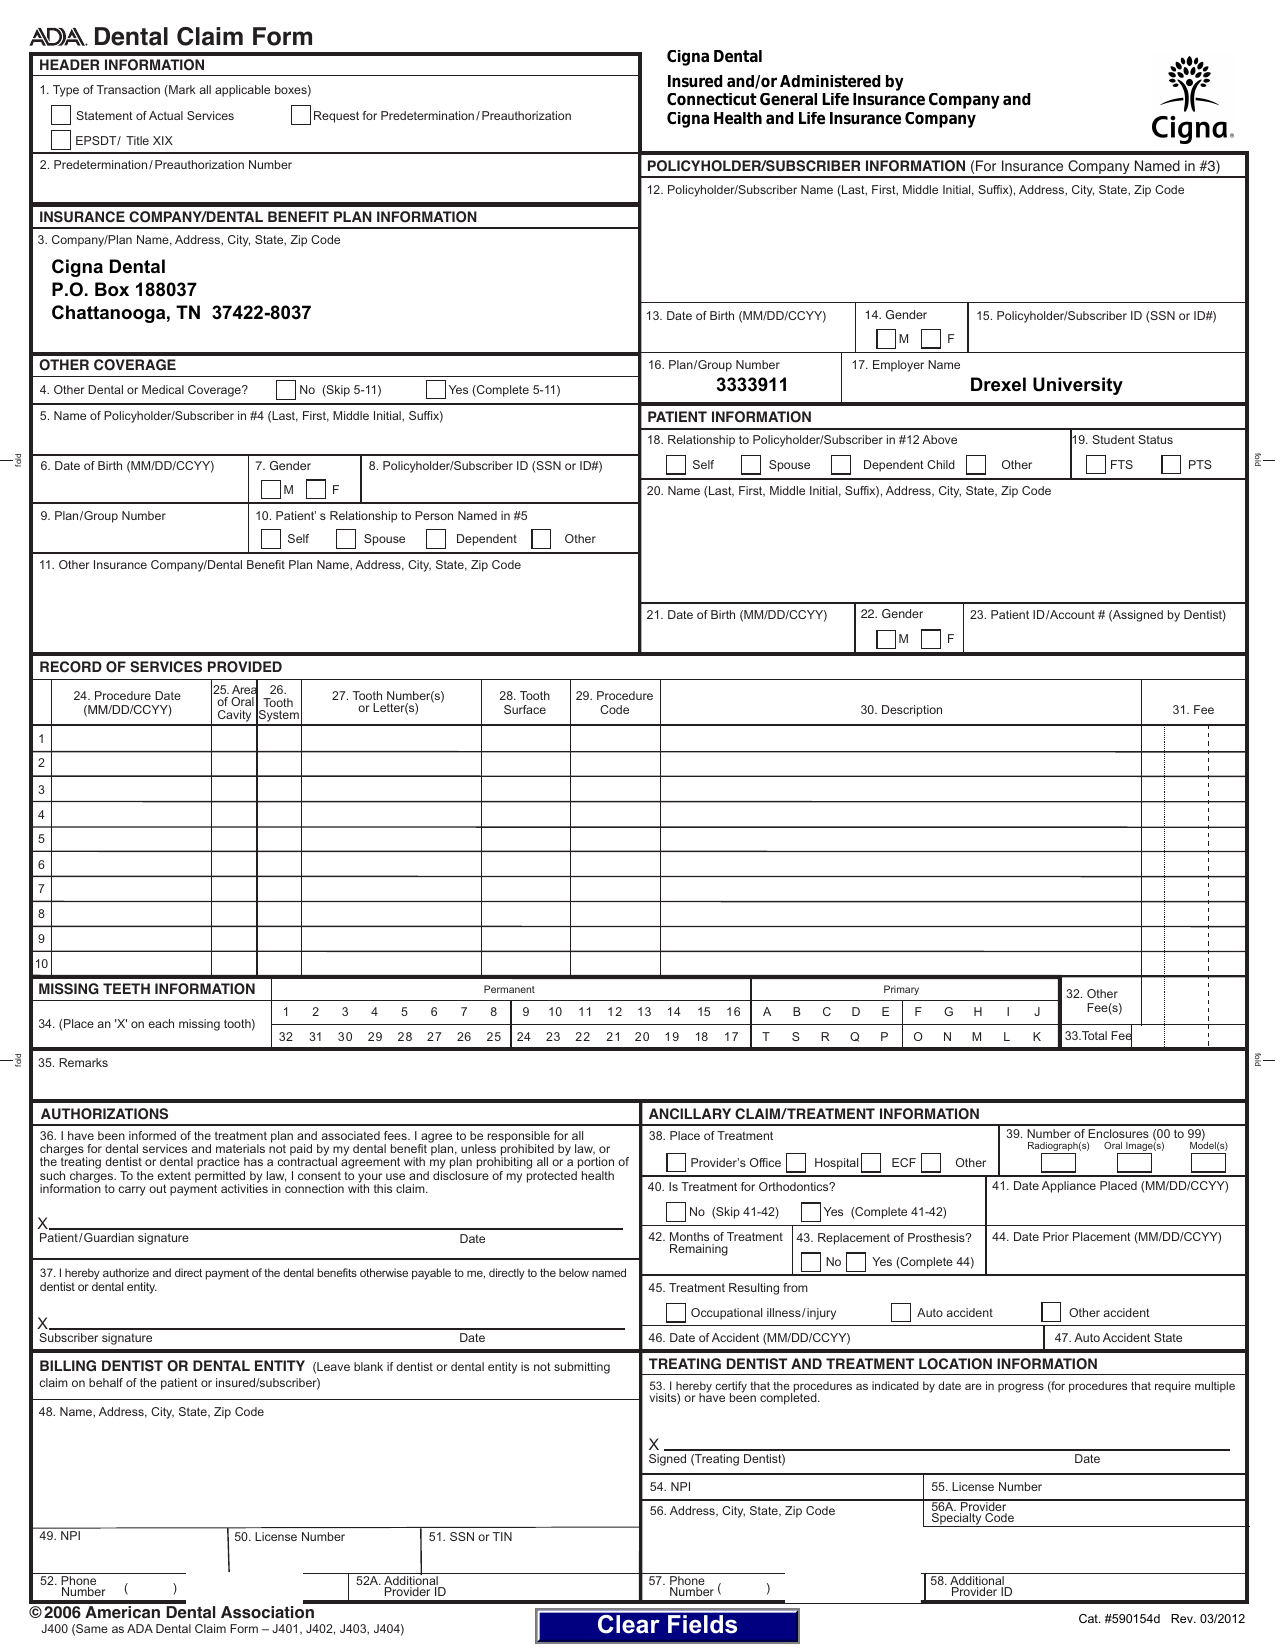
Dental Claim Form
Web the guide of editing blank ada dental claim form online. Patient’s name (first, middle.
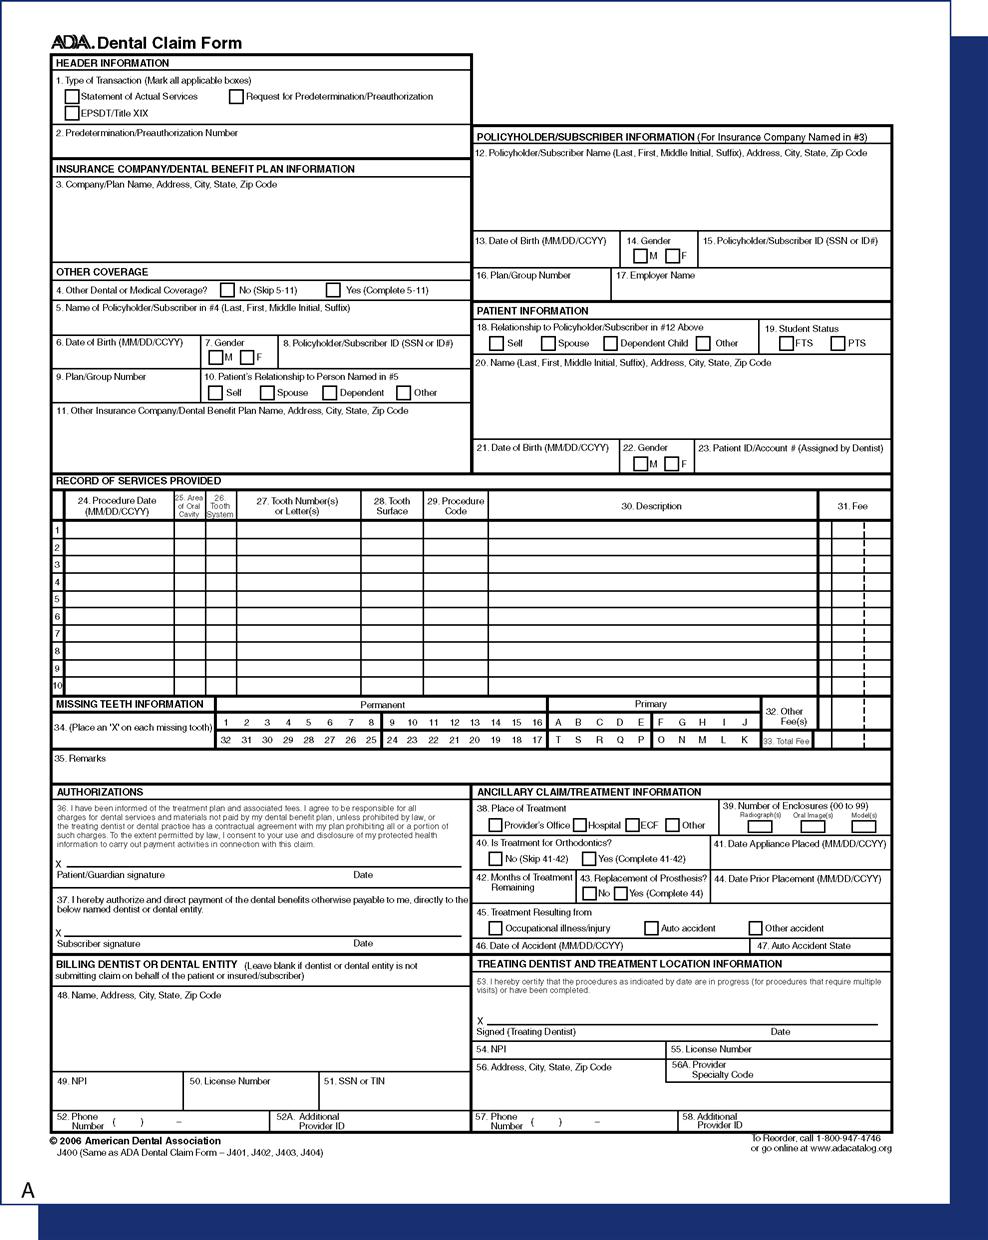
14. Dental Insurance Pocket Dentistry
Web of this form.) s dental claim form please type or print 1. Delta dental.
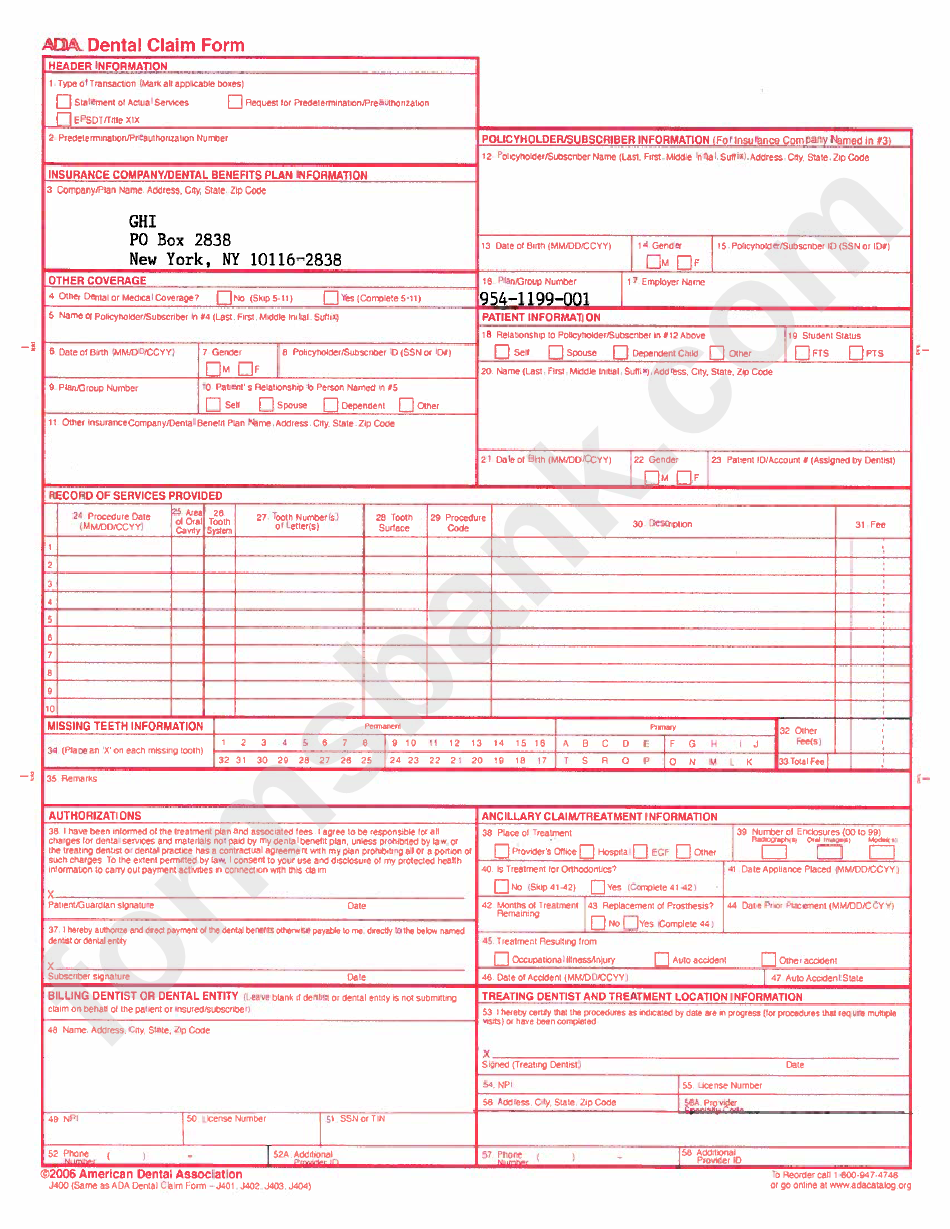
Emblem Health Dental Claim Form printable pdf download
Either complete the form online then print it, or print the form and complete it.
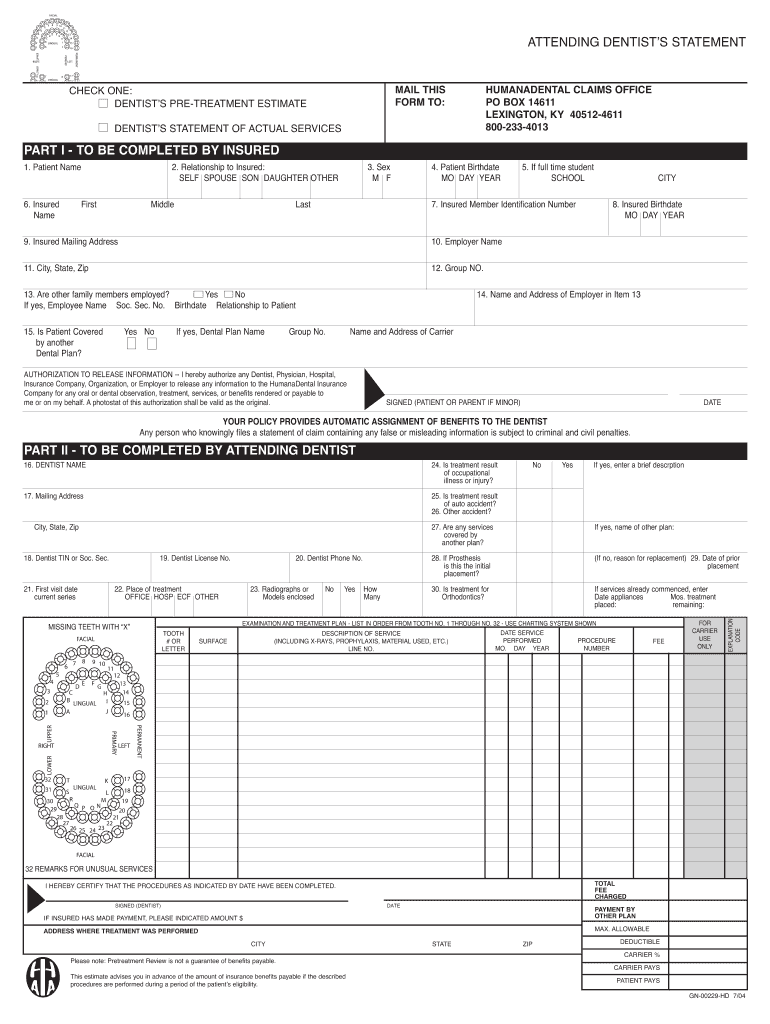
2004 Form Humana GN00229HD Fill Online, Printable, Fillable, Blank
Quickly add and underline text, insert pictures, checkmarks, and symbols, drop new fillable areas, and.
Web online claim form aflac. Web of this form.) s dental claim form please type or print 1. Web humana doesn't require a specific dental claim form. Web a separate, fully completed claim form. Sign the form, attach all. Aetna dental works with claimconnect tm offered by edi health group (ehg) to provide easy access. Ada dental claim form is a document that describes the services provided by a dental provider and provides. Web dental claim form connection dental plus members, providers or office personnel may use this form to submit dental claims to geha. Web printable dental claim form: Web the guide of editing blank ada dental claim form online. Find the sample you require in the collection of legal forms. Web to submit a claim using a claim form: This online claim submission tool is. Delta dental claim form for deltacare® usa claims and encounters. Go through the instructions to find out which data you need to provide.
Quickly Add And Underline Text, Insert Pictures, Checkmarks, And Symbols, Drop New Fillable Areas, And Rearrange Or Remove.
Web printable dental claim form: This online claim submission tool is. Fill out the necessary boxes. Either complete the form online then print it, or print the form and complete it manually.
Your Dentist Will Submit Your Claim Directly To Humana.
Patient’s Name (First, Middle Initial, Last) 4.
This information is required when the diagnosis may affect claim adjudication when specific. Web of this form.) s dental claim form please type or print 1. Delta dental claim form for deltacare® usa claims and encounters. Web edit ada claim form fillable and printable pdf.
Web A Separate, Fully Completed Claim Form.
Use aflac smartclaim® app to initiate your claim process online or track your claim. Download for more information on filing. Fill & download for free get form download the form how to edit and draw up printable dental claim form online read the following. Web open the form in the online editor.